

ANSWER TO THE CLINICAL CASE FROM JULY 18. TASK DIFFICULTY LEVEL: HIGH. Recurrent respiratory infections. Lymphopenia and hypereosinophilia. 👉🏻Correct answer: 3. LATE-ONSET ADENOSINE DEAMINASE DEFICIENCY. Lymphopenia and hypereosinophilia can reflect both primary and secondary immunodeficiency. ❗In HIV infection, high IgE levels and hypereosinophilia are associated with disease severity. Acquired immunodeficiency syndrome (AIDS) is clinically characterized by hepatosplenomegaly, lymphadenopathy, and, unlike congenital immunodeficiency, the presence of hypergammaglobulinemia. ❗In rare cases, mycobacterial tuberculosis can manifest with peripheral eosinophilia, but the clinical response to penicillin makes this hypothesis unlikely. The child’s Mantoux test and QuantiFERON test were normal. ❗Although hypereosinophilia is a hallmark of Churg-Strauss syndrome, typical respiratory manifestations such as treatment-refractory asthma and lymphopenia are absent. ❗❗❗ Recurrent infections, lymphopenia, and hypogammaglobulinemia, as well as the presence of early-onset eczema, are highly indicative of primary immunodeficiency (PID).
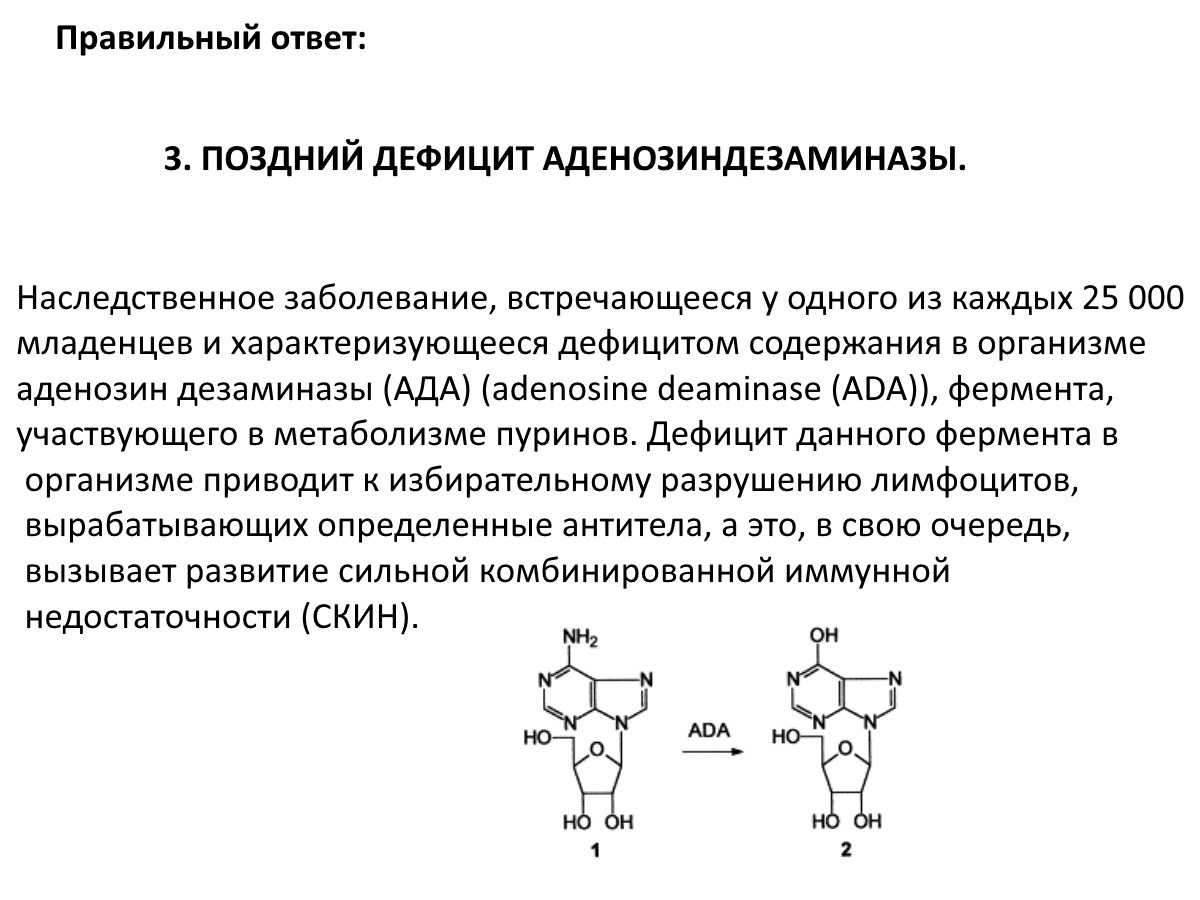
Wiskott-Aldrich syndrome typically presents with intractable diarrhea and eczema and affects boys. X-chromosome inactivation can also lead to a milder phenotype in girls. Thrombocytopenia associated with small platelet volume is necessary for the diagnosis of Wiskott-Aldrich syndrome. Classic adenosine deaminase deficiency manifests with severe lymphopenia. Late-onset adenosine deaminase deficiency matches the clinical picture of this patient: progressive lymphopenia, elevated serum IgE, eosinophilia, recurrent pulmonary infections, and premature eczema. Late-onset adenosine deaminase deficiency presents with recurrent infections starting after 1 year of age. Typical infections include otitis, sinusitis, and upper respiratory tract infections. In addition, autoimmune diseases and allergies are common. Neurological disorders are much more common in adenosine deaminase deficiency compared to other primary immunodeficiencies and include cognitive deficits, behavioral problems, and sensorineural hearing loss. The first-line diagnostic test is based on the assessment of the adenosine deaminase enzyme, namely catalytic activity in hemolysates, extracts of dried blood spots with EDTA or heparin. If adenosine deaminase activity is below 1% of the reference value, the diagnosis is probable. False-negative results may be due to recent red blood cell transfusion. The absence of the adenosine deaminase enzyme leads to the accumulation of deoxyadenosine, a toxic metabolite, which confirms the diagnosis. In the described patient, adenosine deaminase activity was below 1%, and toxic metabolites were elevated. Genetic analysis revealed a c.385G > A p.Val129Met mutation, which has been reported to be associated with delayed-onset adenosine deaminase deficiency. Enzyme replacement therapy prevents the accumulation of toxic metabolites, and most individuals treated with pegylated adenosine deaminase partially restore immune function, which is sufficient to prevent opportunistic infections and other clinical manifestations of immunodeficiency. Other manifestations of adenosine deaminase deficiency, including autoimmune disorders and neurological impairments, do not respond to such treatment. Source: Rezaei N. (ed.). Pediatric Immunology: A Case-Based Collection with MCQs, Volume 2. – Springer Nature, 2019.


