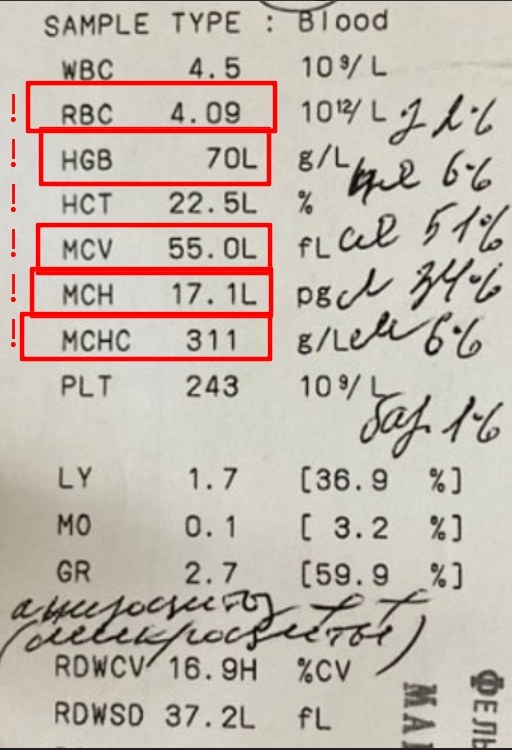
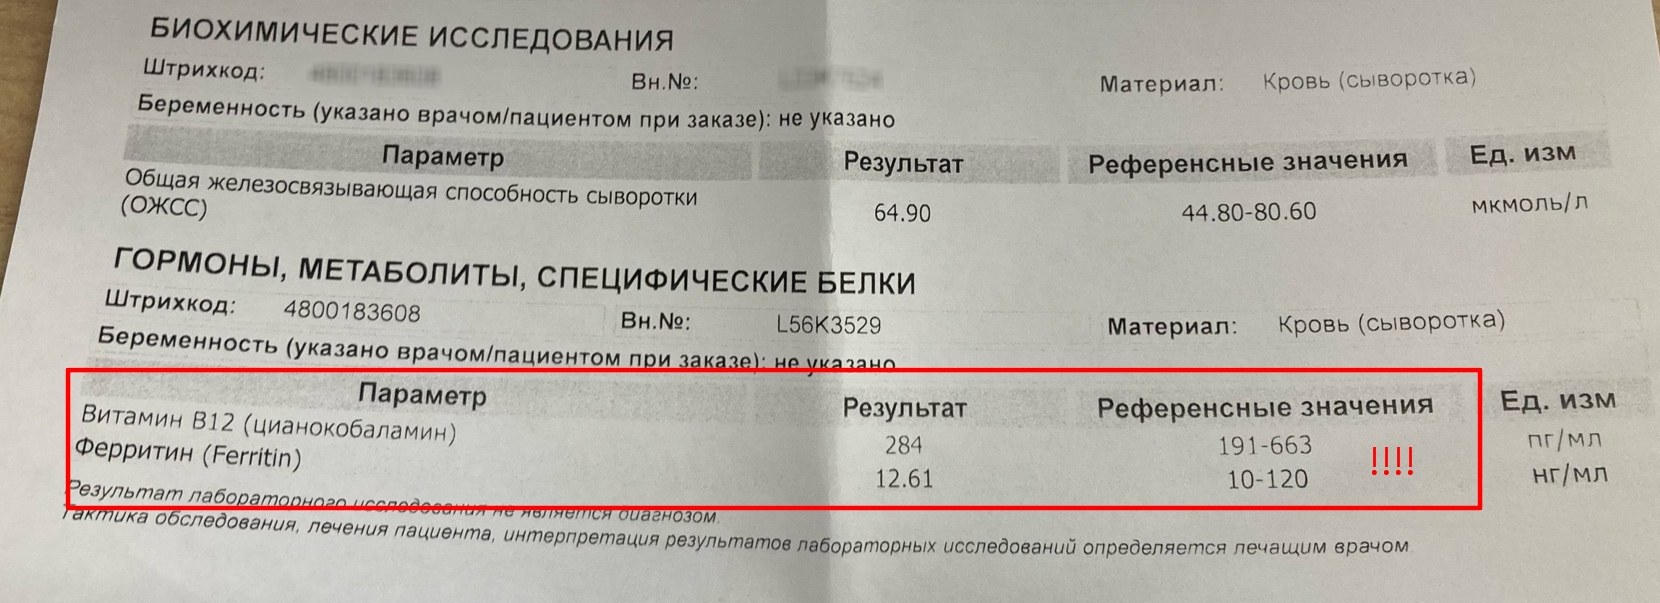
💡B12-deficient anemia or IDA?! 🆘A 45-year-old woman contacted us via messenger for help, asking to review her primary diagnosis made in the Moscow region. ✅Vitamin B12 minimum was 175 pg/mL ✅Ferritin 8.75 ng/mL ✅Serum iron 49 µmol/L ✅Hemoglobin 70 g/L ✅Red blood cells - 4.09 million/µL ✅MCV 55 fL ✅MCH 17.1 pg ✅MCHC - 311 g/L Based on these tests, the doctor recommended the patient continue intramuscular cyanocobalamin (vitamin B12) injections. ⚠BASED ON WHICH INDICATOR WAS THE DIAGNOSIS OF B12-DEFICIENT ANEMIA MADE? ⚡It’s hard to say… Probably the attending physician was confused by the elevated serum iron level – 49 µmol/L. And at this stage, IDA was ruled out. Then, apparently, the doctor’s attention turned to vitamin B12, which was at the lower limit of normal. ❗But why, despite the lack of positive dynamics during vitamin B12 treatment, does the doctor still recommend continuing cyanocobalamin injections?? 📢Let’s look more closely at the laboratory test results. Microcytic hypochromic anemia (severe) with a normal red blood cell count, with a reduced ferritin level (!) and a normal vitamin B12 level. This is proven iron deficiency anemia! All criteria were met, except for the serum iron level. Although we know that serum iron can be elevated due to iron-rich food intake before the test. Perhaps the doctor did not know that a reduced ferritin level is the gold standard for diagnosing iron deficiency anemia. ✅The patient was advised to critically evaluate the prescribed treatment and seek a second opinion from an in-person hematologist, gastroenterologist, and gynecologist. Also, due to enlarged inguinal lymph nodes, an oncologist consultation is necessary. It is important to find the source of chronic bleeding.
Differential Diagnosis of Iron Deficiency and B12 Anemia
A clinical case review: differentiating microcytic iron deficiency anemia and vitamin B12 deficiency based on MCV and ferritin levels.